Evidence-Based Surgical Excellence

Clinical Case Studies & Surgical Outcomes

Explore documented surgical cases treated at F.O.R. Ortho & Neuro Hospital. From high-energy polytrauma and neurovascular compromise to complex periprosthetic fractures and geriatric joint reconstruction, see authentic pre-operative and post-operative radiographic outcomes.

1,000+
Joint Replacements Performed
24/7
Accident & Fracture Trauma Care
Twin OT
Ultra-Clean Laminar Airflow
100%
In-House Diagnostic & CT Scan
Documented Surgical Series

Featured Clinical Records

Each case details the diagnostic challenge, clinical reasoning, surgical strategy, and long-term functional recovery achieved under our senior consultants.

#1Complex Trauma & Neurovascular Injury
Patient: 28 Years, Female•Severe Road Traffic Accident (RTA)
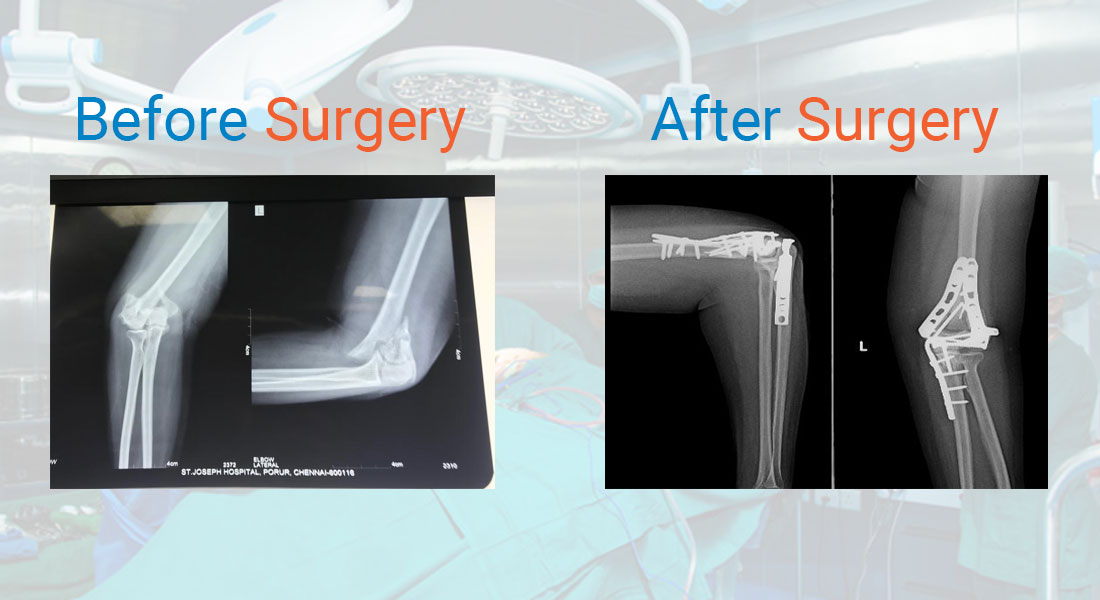
X-Rays for Distal Humerus Fracture with Radial Nerve Paralysis
Pre-Op & Post-Op RadiographsF.O.R. Archive
Surgical Leadership:

Dr. P. Elangovan (Chief Orthopaedic Consultant) & Trauma Surgery Team

Request Specialist Opinion on Similar Case

Distal Humerus Fracture with Radial Nerve Paralysis

A 28-year-old female sustained a shattered distal humerus fracture with complete drop-wrist caused by traumatic radial nerve paralysis following a road traffic accident. The team successfully reconstructed the elbow joint and released the trapped radial nerve, resulting in complete motor recovery and elbow function.

The Clinical Problems Tackled:

  • Severely comminuted intra-articular distal humerus fracture demanding rigid anatomical reconstruction.
  • Primary radial nerve palsy requiring urgent neurolysis without iatrogenic nerve transection.
  • Achieving absolute joint stability to facilitate early rehabilitation and prevent elbow joint stiffness (ankylosis).

Surgical Protocol & Fixation:

  • Open Reduction Internal Fixation (ORIF) performed via a posterior transolecranon approach.
  • Careful exploration of the radial nerve — nerve was identified to be severely kinked and trapped across fracture spikes; neurolysis and safe decompression performed.
  • Rigid dual-plate anatomical fixation with pre-contoured locking plates to achieve rigid columnar stability.
  • Immediate post-operative physiotherapy initiated with passive range of motion.

Clinical Outcome & Recovery:

Full radial nerve neurological recovery with complete wrist and finger extension. The patient regained excellent elbow range of movement (ROM) and returned to normal daily activities without residual deformity.
#2Joint Replacement & Geriatric Orthopaedics
Patient: 71 Years, Female•Domestic Fall at Home (Diabetic & Hypertensive)
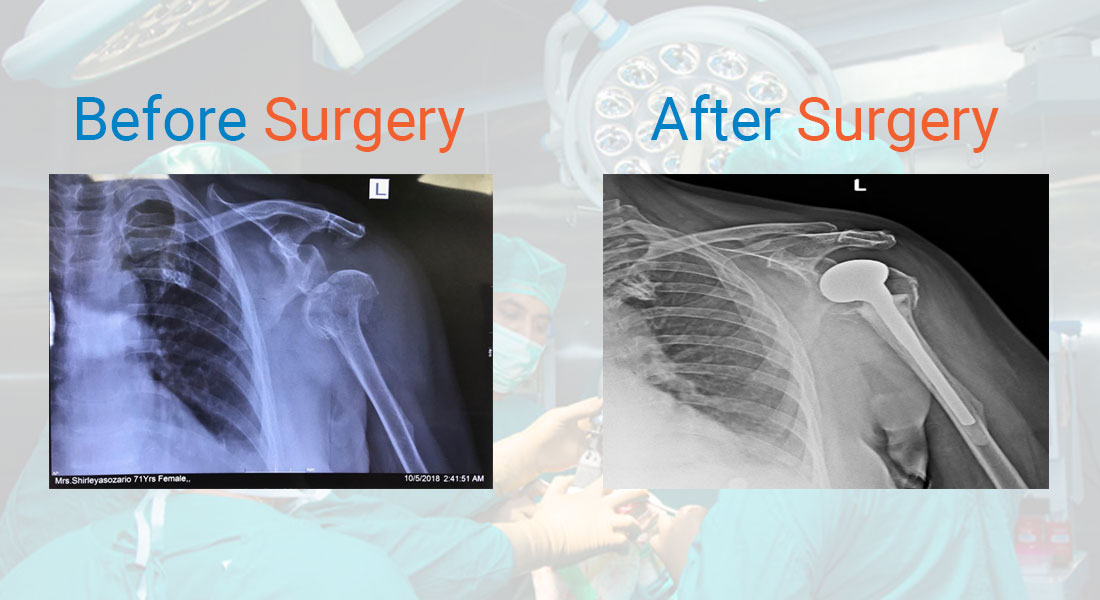
X-Rays for Primary Hemiarthroplasty of the Shoulder in Geriatric Osteoporotic Fracture
Pre-Op & Post-Op RadiographsF.O.R. Archive
Surgical Leadership:

Dr. P. Elangovan (Chairman & Chief Joint Replacement Surgeon)

Request Specialist Opinion on Similar Case

Primary Hemiarthroplasty of the Shoulder in Geriatric Osteoporotic Fracture

A 71-year-old diabetic and hypertensive patient presented with a shattered proximal humerus fracture after a domestic fall. In elderly osteoporotic bone, screw fixation carries a very high rate of failure. A primary shoulder hemiarthroplasty was performed, enabling fast recovery and discharge on Day 4.

The Clinical Problems Tackled:

  • Severe osteoporotic bone where standard plate and screw purchase would easily cut out and fail.
  • Severely comminuted 4-part humeral head fracture with disrupted blood supply, carrying extreme risk of avascular necrosis (AVN).
  • Elderly patient with multiple medical co-morbidities requiring early mobilization and minimal hospital stay.

Surgical Protocol & Fixation:

  • Primary Shoulder Hemiarthroplasty selected over prolonged open reduction internal fixation to guarantee lasting joint function.
  • Precise retroversion positioning of the humeral stem and anatomical tuberosity reconstruction using heavy non-absorbable sutures.
  • Minimal soft-tissue trauma protocol enabling rapid post-surgical healing.
  • Patient mobilized out of bed on Day 2 with assisted pendulum exercises.

Clinical Outcome & Recovery:

Discharged on the 4th post-operative day. Pain-free shoulder joint with restoration of functional range of motion for daily living. Follow-up X-rays confirm anatomical tuberosity healing around the prosthesis.

#3Revision Joint Reconstruction & Complex Trauma
Patient: 73 Years, Male•Slip and Fall Following Previous Total Hip Replacement
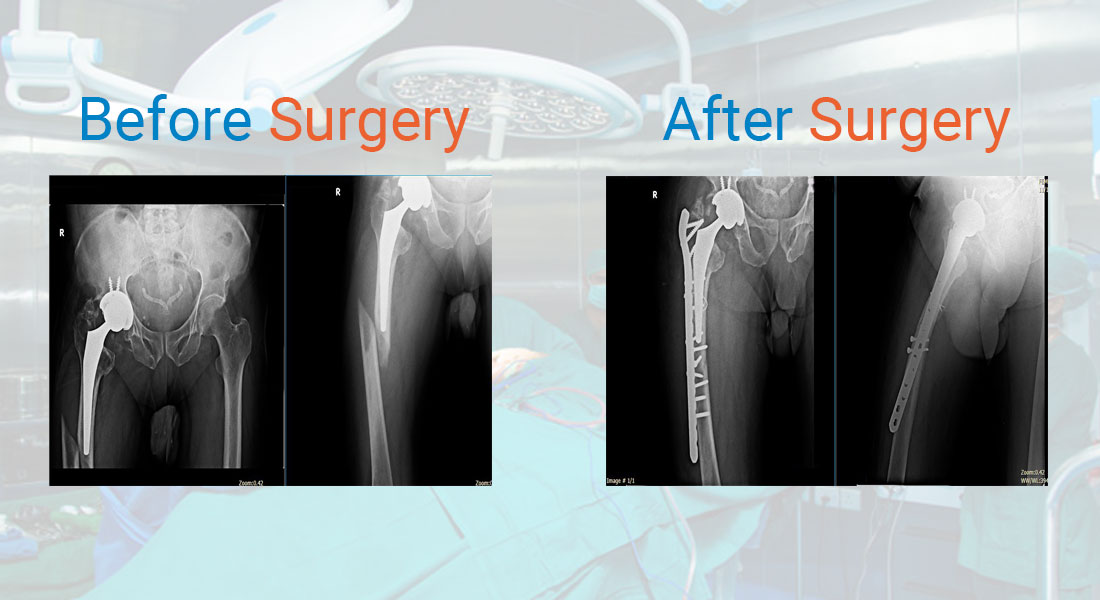
X-Rays for Periprosthetic Femur Fracture Complicating Total Hip Replacement
Pre-Op & Post-Op RadiographsF.O.R. Archive
Surgical Leadership:

Dr. P. Elangovan & Joint Reconstruction Surgical Team

Request Specialist Opinion on Similar Case

Periprosthetic Femur Fracture Complicating Total Hip Replacement

A 73-year-old male with a previously implanted Total Hip Replacement suffered a high-energy periprosthetic femur fracture surrounding the femoral stem. The surgical team successfully stabilized the fracture with a long trochanteric plate and lag screws, saving the hip implant without requiring a major revision.

The Clinical Problems Tackled:

  • Intramedullary space occupied by the hip prosthetic stem, making standard screw insertion highly challenging.
  • Severe osteoporotic cortical bone prone to propagate fractures under surgical stress.
  • Preserving stem stability while achieving absolute biological fracture union.

Surgical Protocol & Fixation:

  • Extended lateral surgical approach preserving soft tissue sleeve and blood supply.
  • Application of an anatomically contoured long trochanteric locking compression plate spanning well beyond the fracture zone.
  • Use of strategic bicortical lag screws and periprosthetic cable grips around the hip stem for rigid neutralization.
  • Careful bone grafting at the comminution site to encourage biological osteosynthesis.

Clinical Outcome & Recovery:

Solid radiological bone union achieved. The hip prosthesis remained stable and well-fixed. The patient regained independent assisted walking and progressed to walking unassisted without limp or leg length discrepancy.

#4High-Energy Trauma & Soft-Tissue Preservation
Patient: 36 Years, Female•High-Speed Road Traffic Accident (RTA)
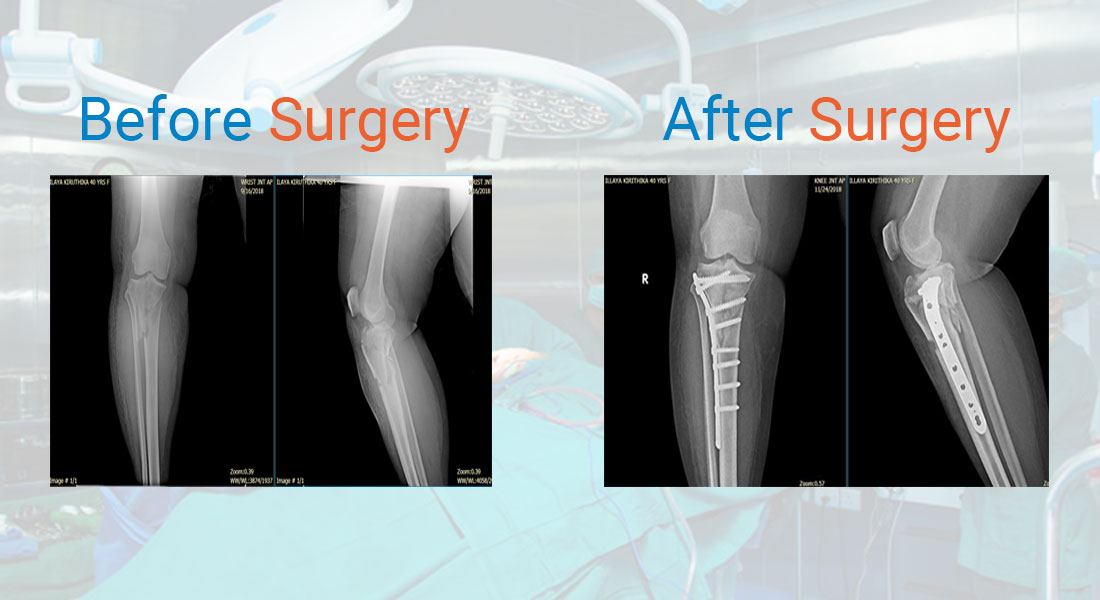
X-Rays for Complex Comminuted Proximal Tibia Fracture with Severe Soft-Tissue Injury
Pre-Op & Post-Op RadiographsF.O.R. Archive
Surgical Leadership:

Dr. P. Elangovan & Trauma Care Team

Request Specialist Opinion on Similar Case

Complex Comminuted Proximal Tibia Fracture with Severe Soft-Tissue Injury

A 36-year-old female was rushed to F.O.R. Hospital with a shattered proximal tibia and severe soft tissue compromise including hemorrhagic fracture blebs. Rushing into immediate open surgery through compromised skin would have caused skin necrosis and infection. A staged surgical protocol delivered complete limb salvation.

The Clinical Problems Tackled:

  • Severe soft tissue compromise with tense swelling and fracture blebs that precluded immediate open surgery.
  • Severely fragmented articular surface of the proximal tibia threatening future knee joint function.
  • Extreme risk of deep osteomyelitis and skin flap breakdown if surgical timing was misjudged.

Surgical Protocol & Fixation:

  • Staged Damage Control Protocol: Initial temporary stabilization and aggressive soft tissue elevation, dressing, and edema reduction for 7 days until the 'wrinkle sign' appeared.
  • Definitive surgical reconstruction performed via gentle anatomical approach once skin integrity was restored.
  • Articular elevation and rigid locking plate fixation restoring anatomical joint line and mechanical axis.
  • Supervised non-weight bearing knee motion started immediately post-surgery.

Clinical Outcome & Recovery:

Primary wound healing achieved with zero skin breakdown or infection. The proximal tibia consolidated solidly with preserved articular congruity. Patient is currently walking full weight-bearing without support.

Second Opinion & Complex Cases

Facing a Complex Fracture or Revision Surgery?

Bring your X-rays and MRI scans to F.O.R. Ortho & Neuro Hospital for an in-depth surgical evaluation with Dr. P. Elangovan and our expert team. Cashless TPA insurance accepted.